The physicians, the structure, the LegitScript application, the pharmacy, the patient portal, and the marketing that fills it. Without hiring a doctor, forming the entity yourself, or giving up a share of your clinical revenue.
Written, in your inbox within 24 hours. Yours to keep either way.Compounded medications, including peptide therapies and GLP-1 medications, are not FDA approved.
Three things sit between your audience and a lawful prescription. Each one stops a launch cold, and none of them is fixed by better ads.
A named medical director licensed in your state, written protocols for every service on your menu, delegation and supervision, good faith exams and chart review. Naming a physician is the easy part. The role carries real license exposure.
Who owns the clinical entity, who signs the order, and how the management fee is calculated. Texas requires an MD or DO with written delegation. New York prohibits percentage based management fees. California restricted outside control of medical practices from January 2026. None of it is portable.
Meta and Google gate prescription telehealth, ban condition targeting, and close retargeting to you entirely. The FTC, Utah and LA County sued Hims in July 2026 over health events in the pixel. So the storefront goes up and nothing happens, because the channel meant to fill it was never open.
Click through what gets stood up on your behalf, and what you end up owning at the end of it.
Medical direction, nationwide
An MD or DO named as your medical director, with protocols, delegation and supervision. Providers issue orders under their own clinical judgment.
Every clinical decision sits with the licensed provider. KNWN4 does not practise medicine.
The structure your state actually requires
Who owns the clinical entity, who signs the order, and how the management fee is calculated. None of it is portable between states.
Three examples, not the whole map. Which rules apply to you depends on your state, your entity and your service list, and should be confirmed with your own counsel.
The LegitScript application
We prepare the site, the claims, the policies and the evidence, then run the submission and answer the rounds of questions that follow.
We never promise certification, and nobody honest can. We control the quality of the application, not the outcome.
Pharmacy, lab and fulfilment
503A and 503B relationships, lab draws and result review, and the logistics that put a box on a doorstep.
Compounded medications, including peptide therapies and GLP-1 medications, are not FDA approved.
The patient portal, under your brand
Intake, orders, refills, messaging and records. Everything ships on your domain and under your name, and the patient relationship stays yours.
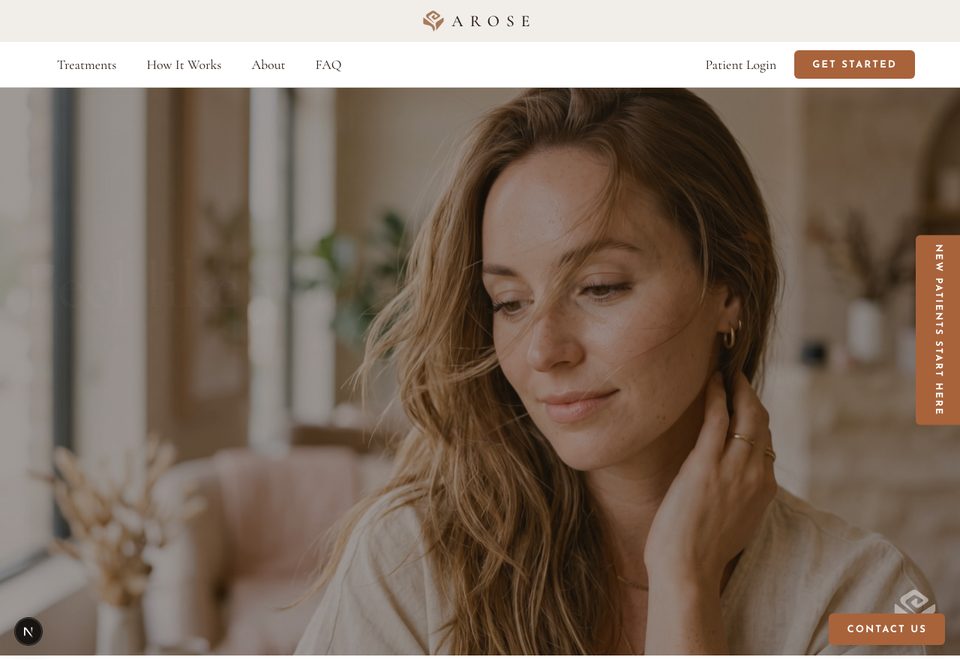
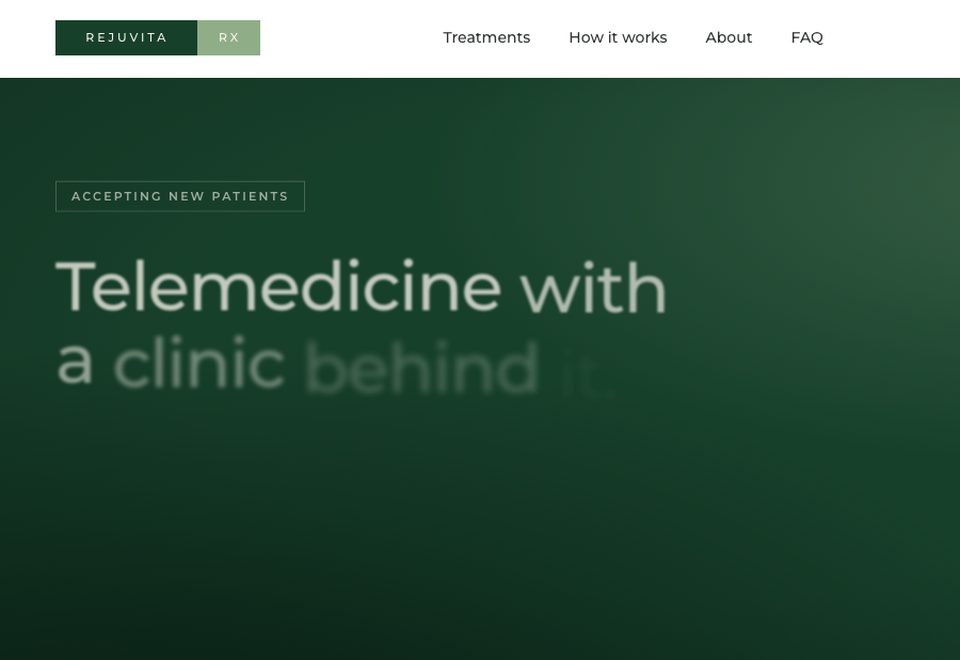
Two storefronts built for KNWN4 clients. If we part ways you keep the site, the list and the records.
The marketing that fills it
The channel is gated here. You cannot target by condition, retargeting is closed to you, and most funnels in this category were built for a category where both are open.
Advertising approvals are decided by Meta and Google, never by us.
Most operators are not one piece away from this. They are nine pieces away, and the pieces have to be bought from seven different people who all point at each other when something breaks.
An MD or DO named as your medical director, with the protocols, delegation and supervision your state actually requires.
Licensed physicians in the states you operate in, issuing orders under their own clinical judgment.
A professional corporation where the state requires one, and a management agreement written not to split clinical revenue.
Structured intake, provider review and a documented decision to approve, decline or ask for more.
We prepare the site, the claims, the policies and the evidence, and we run the submission. LegitScript decides the outcome, not us.
503A and 503B relationships, lab draws and result review, and the logistics that put a box on a doorstep.
Intake, orders, refills, messaging and records. Your brand on the front, a HIPAA aligned platform underneath.
The part the clinical companies do not do and most agencies cannot survive. Ads, creative, email and SMS, written for a category that rejects most of it.
What a patient costs to acquire and what that patient is worth by month three, with repeat revenue counted separately.
One line first, built properly and proven to pay, then the next. Launching six at once is how operators end up with six half funnels and a protocol binder nobody follows.
Compounded medications, including peptide therapies and GLP-1 medications, are not FDA approved. Which service lines you can lawfully offer, who may perform them, and how you are allowed to advertise them all vary by state and by product classification. KNWN4 builds and runs the brand and the marketing. Clinical structure, prescribing and dispensing sit with licensed physicians, providers and pharmacies, and every clinical decision is theirs.
Priced so that nobody in this arrangement earns more when a patient is prescribed more. That is not a courtesy, it is the reason the structure holds up.
Paid to the physician led partner who supplies the medical director, the provider network, the protocols and the good faith exams.
One fee to build the brand, the patient site, the intake and the flows. Then a monthly to run the acquisition and own the number.
No share of clinical revenue, no percentage of your patient billings, and no fee that moves because a provider approved more.
The two numbers depend on your state, your service list and what already exists. You get both in writing within two days of the call, and the call costs nothing.
Tell us what you run and where the clinical side stands. You get the shape of the answer here, and the written version within 24 hours of the call.
What do you run today?
This decides which service line is worth opening first.
Where does the clinical side stand?
This changes everything we would recommend, so it is worth being honest about.
Here is the shape of it
Not a quote. The written plan on the call carries your state, the timeline and both numbers.
Thirty minutes. Tell us where you operate and what you want to offer, and we will tell you what it actually takes. A plan within 24 hours, a price within two days, or an honest no.
